In 30 seconds
Denys Linkov explains why medical claims are difficult to process: records vary by provider and jurisdiction, arrive in multiple formats and may contain duplicates, omissions or conflicting diagnoses. He argues that data quality and human review are prerequisites for useful AI. He describes the MLCR benchmark, a layered extraction pipeline and potential portfolio analysis. He distinguishes the company’s specific results and aspirations from proven industry-wide impact.
- 1Forms differWorkers’ compensation forms vary across jurisdictions.
- 2Clean the dataDuplicates, mixed records and poor scans complicate claims.
- 3Find missing evidenceA note may refer to a report absent from the case file.
- 4Evaluate claims reasoningMLCR tests different questions with accuracy and completeness measures.
- 5Look across claimsStructured data can support portfolio analysis, subject to its quality.
- 6Keep human oversightThe system flags issues for people; compliance requires separate assessment.
Takeaways
- Digitization and reliable data are prerequisites for effective AI applications.
- Duplicate, mixed and missing records can affect both privacy and decisions.
- Evaluate accuracy and completeness against expert-validated answers.
- Human reviewers need evidence and oversight throughout the process.
- Cross-claim analysis inherits the limitations of upstream data.
- Customer case studies do not establish industry-wide outcomes.
Read the edited text by chapter
Digital transformation and claims
Linkov introduces the unfinished data work behind enterprise AI.
I lead AI at Wisedocs, where we work on complex medical claims. I want to connect technology decisions to patient and claimant experience, not just business metrics.
Many organizations are trying AI before completing earlier digital transformations. Cloud migrations, data lakes and consistent data practices are still unfinished, so the prerequisites for useful applications need attention.
Paper remains part of medical and insurance workflows. A stack of paper can support an individual claim, but comparing information across claims is difficult when documents are not available as usable data.
Fax is also still used, sometimes converted into digital formats after receipt. That may help ingestion but does not by itself solve the larger problem of exchanging healthcare information.
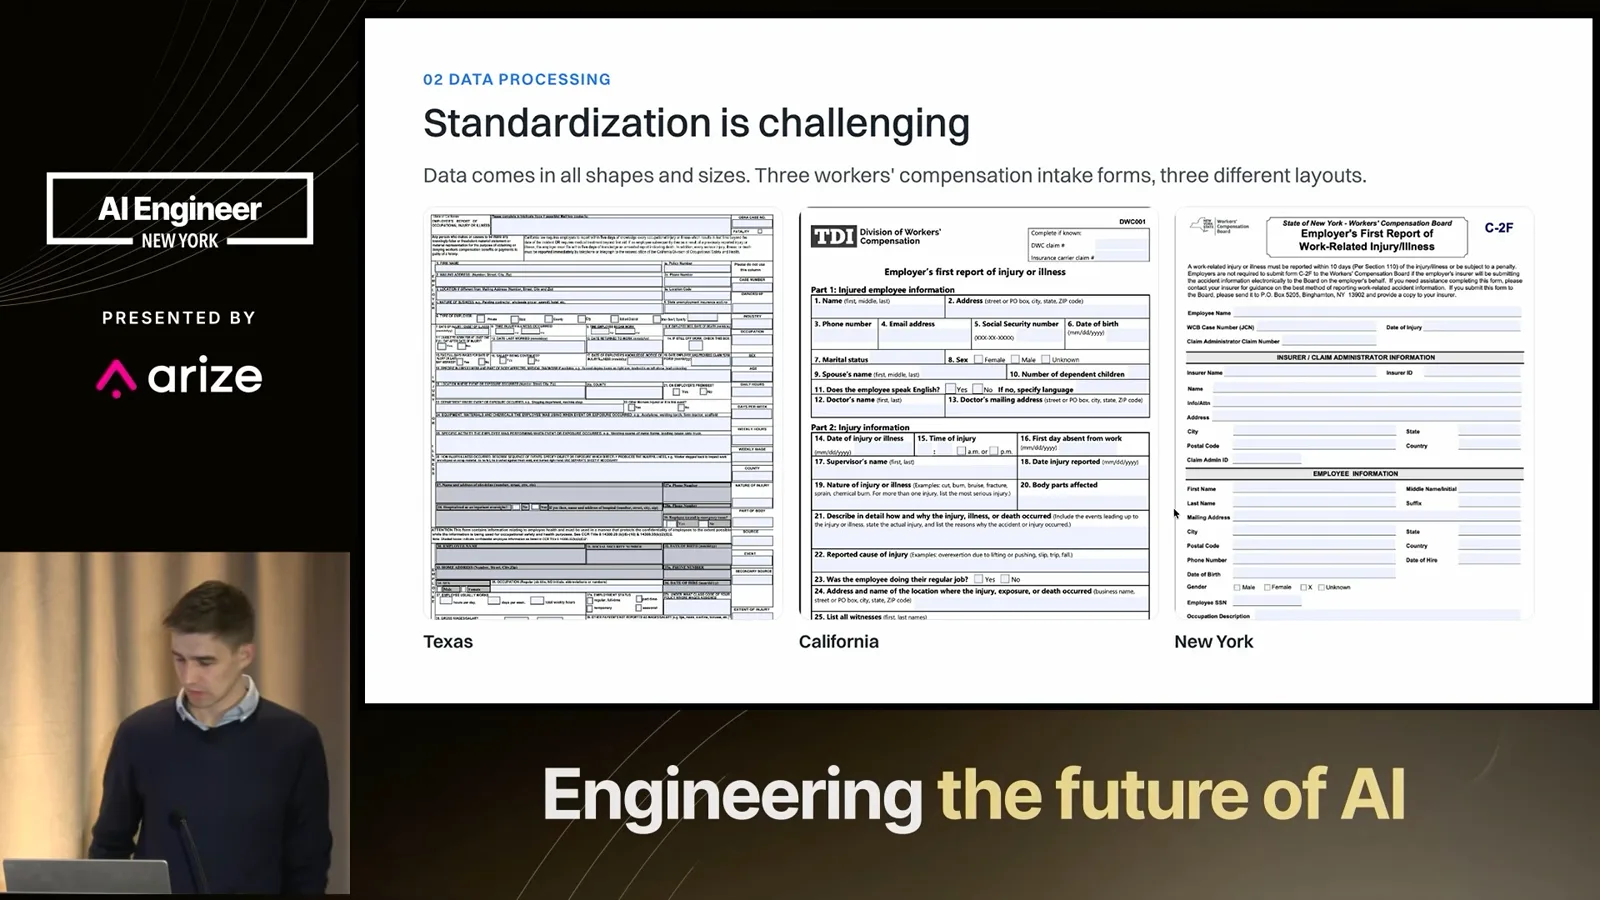
Workers' compensation forms illustrate the lack of standardization. Forms from different states have different layouts and ask for different information, and versions change over time.
Insurers watch measures such as loss ratios and expenses, but a financial metric is only part of the problem. Start with the outcome to improve and choose AI only if it is suitable.
A useful AI program needs clear goals, skilled people, governance, security, infrastructure and data. Even provisioning a system or selecting a vendor can take time in a large enterprise.
An executive might ask for an ideal dataset linking a patient's condition to recent provider outcomes. Answering that question assumes the underlying information exists, can be joined correctly and is suitable for the comparison.
Why medical claims are complex
He describes treatment, coverage and litigation handoffs.
My focus is complex medical claims in property and casualty insurance, including auto liability and workers' compensation. Injury claims can involve treatment, insurers, employers and legal processes.
A claim may take weeks or years depending on its complexity, regulation and litigation. Reducing delays could improve the experience, but a tenfold reduction is an aspiration, not an established result.
The medical journey includes diagnosis, specialists, coverage, review of treatment, billing, payment and follow-up care. Each handoff adds potential delay, and different specialists may disagree.
Adjuster turnover, repeated data processing and the stress experienced by an injured claimant can all complicate the process. The goal is to use technology to help people navigate it.
A workers' compensation case starts with reporting an injury and filing a form, followed by treatment and related documentation. My sample cases are synthetic, but illustrate the kinds of records encountered.
Bills and progress notes vary by provider, and records arrive as PDFs, email or fax rather than a consistent electronic feed. Conflicting observations can make a claim harder to review.
Litigation adds another layer of incentives and delay. Repeated or suspicious submissions must be investigated; a duplicate alone is not evidence of fraud.
Data quality and missing records
Duplicates, mixed files and gaps create operational and privacy risks.
The outcomes I want to keep in view are care quality, cost, speed and experience. I organize the technical work into clean data, analysis within a claim and analysis across claims.

Common data problems include duplicates, records belonging to another patient, poor scans and handwriting. Mixed records raise privacy risks and can also lead reviewers to make decisions using the wrong person's history.
Copying information between notes and inconsistent electronic record implementations contribute to the problem. Even digital systems can contain awkward fields and make information difficult to extract.
Some organizations fall back to fax or PDF when extraction is hard. AI and digital transformation can help, but data quality also depends on upstream practices.
Detecting duplicates is a practical defense against repeatedly processing the same material. Follow-up submissions may have innocent causes, so systems should identify them without assuming intent.
Claims can be extremely large and include images, radiology reports and other formats. I encountered an eight-gigabyte PDF; it is not realistic to assume every such file fits easily into a model's context or a PDF viewer.
A progress note might refer to an X-ray that is missing from the package. Finding the gap matters because the missing report can change how a reviewer understands care, billing or the case timeline.
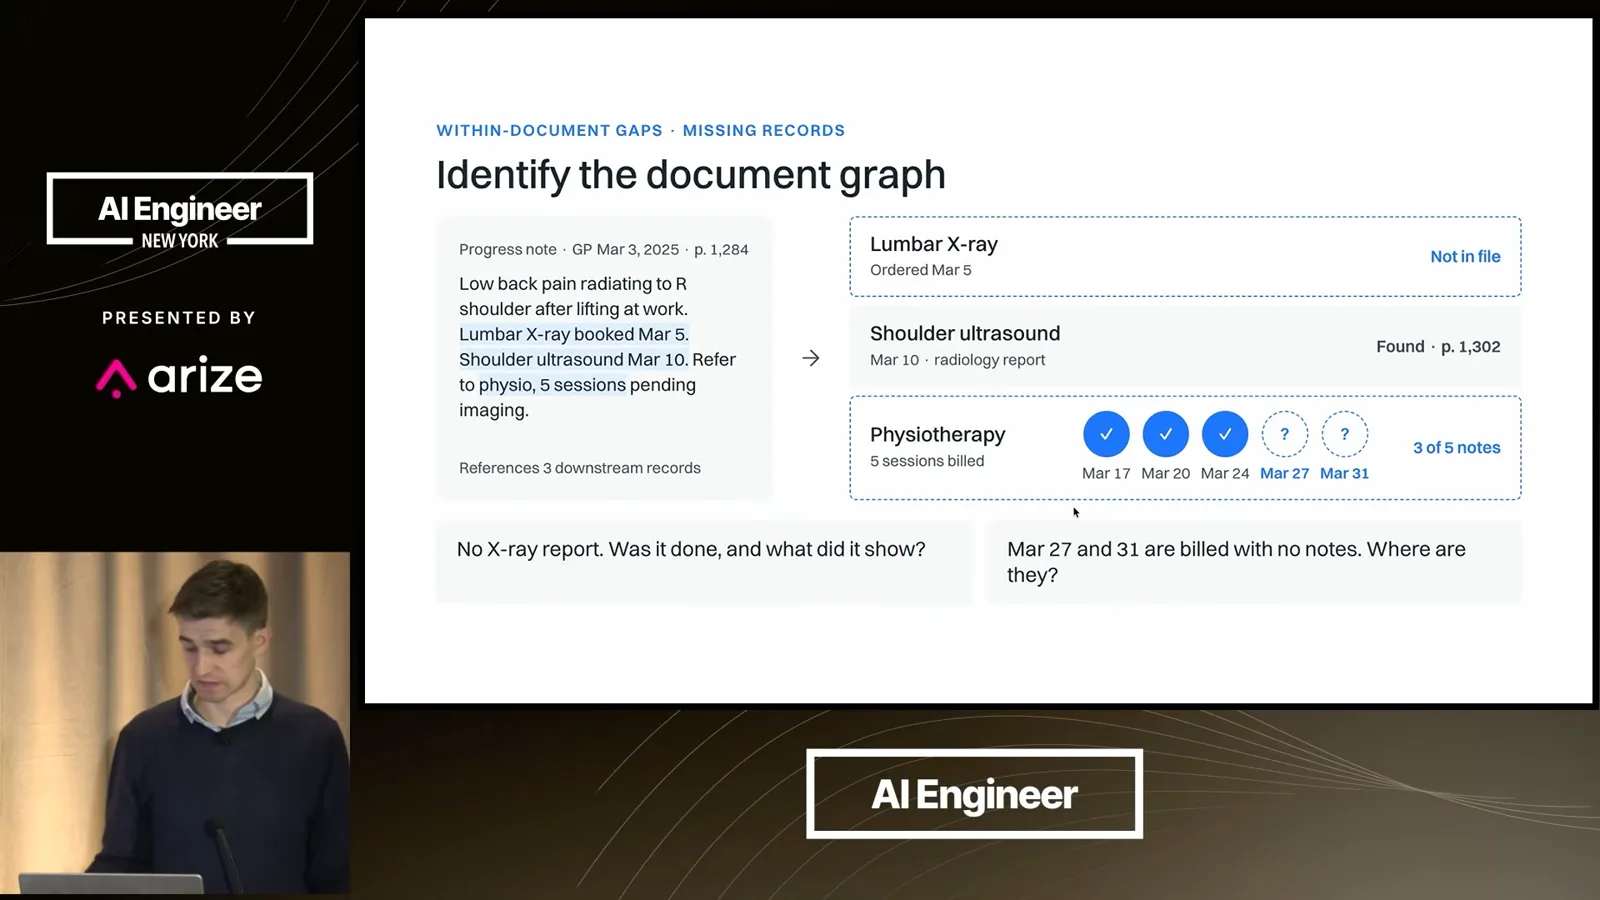
An adjuster may handle many cases at once. A system that flags missing records can support follow-up, but it should surface the evidence for a person to check.
Different doctors can give conflicting diagnoses. An independent medical evaluation may be requested to review the file, adding another specialist and another handoff to the process.
Evaluating medical claims reasoning
He explains MLCR and the importance of accuracy, completeness and expert review.
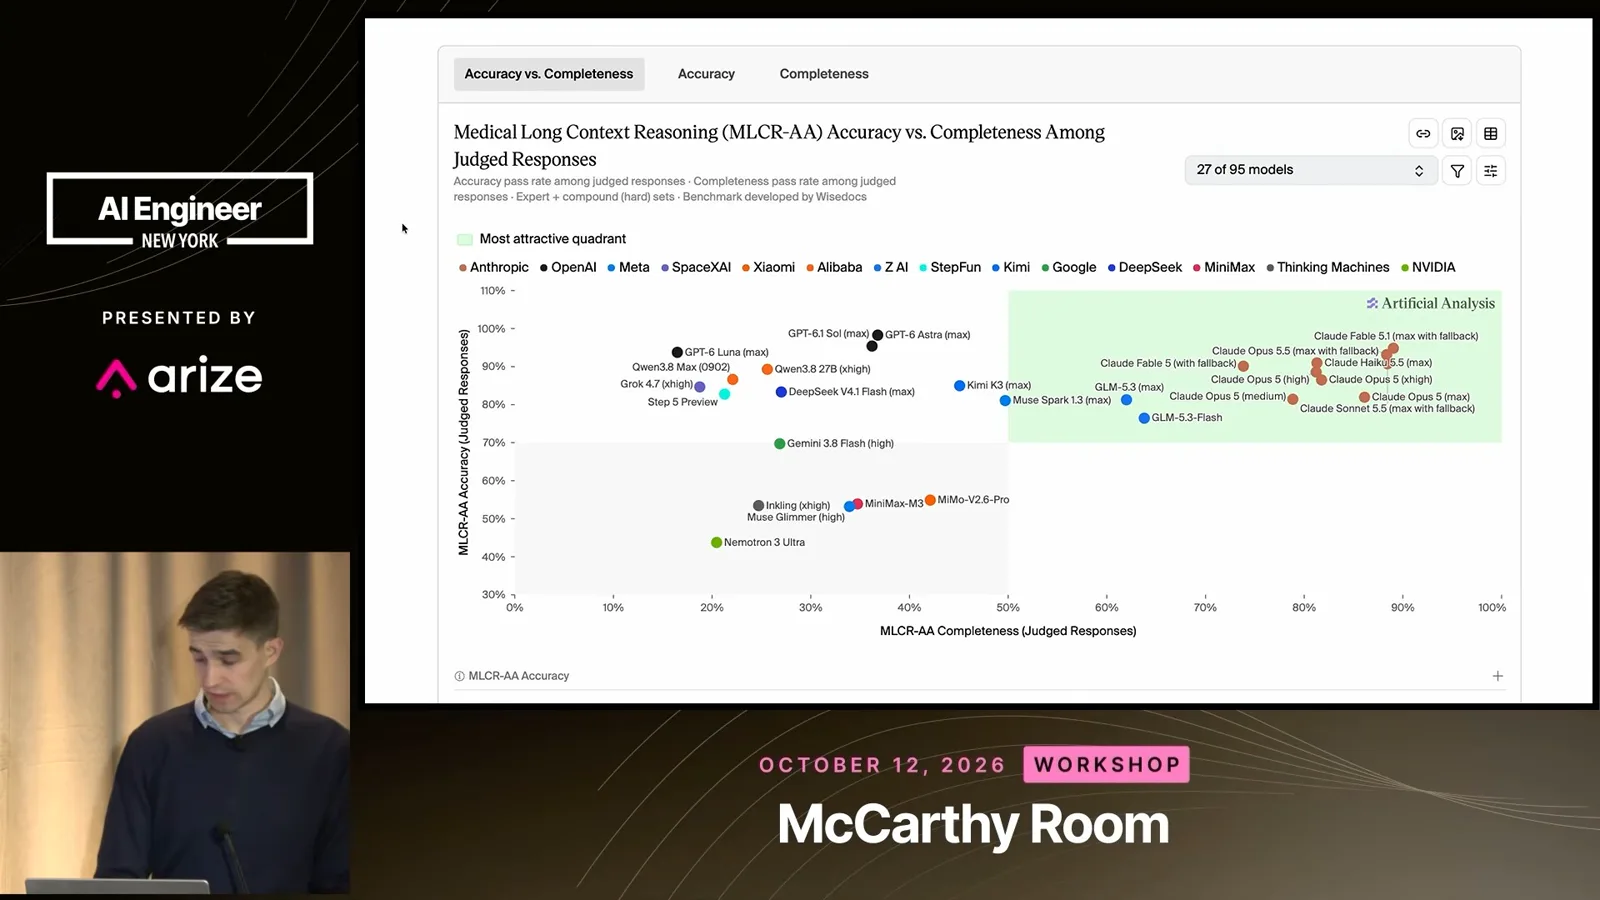
We built the Medical Long Context Reasoning benchmark, MLCR, with Artificial Analysis to assess questions over medical claims. The tasks range from identifying an injury to more complex questions about treatment and capacity.
Some questions assume a fact that is not actually in the record, creating a risk of hallucination. The benchmark has public simpler tasks and a private set for harder evaluation, according to our description.
We assess conciseness, accuracy and completeness against expert-validated answers, using calibrated model judges. A correct answer can still omit relevant facts; evaluation must consider more than one dimension.
In the particular benchmark and configurations shown, Linkov reports that scores improved substantially over a few months. The numbers are tied to that evaluation, not evidence of performance on every real claim.
The demonstrated results show accuracy and completeness tradeoffs across models. Our system keeps a human in the loop, and we calibrate judges and involve domain experts rather than relying on a model's self-assessment alone.
Insights across claims
He discusses geographic, cost and provider analysis.
Once individual claims are structured, a company can examine patterns across a portfolio: types of injury, geography, costs and involved providers. Errors upstream can contaminate all of these analyses.
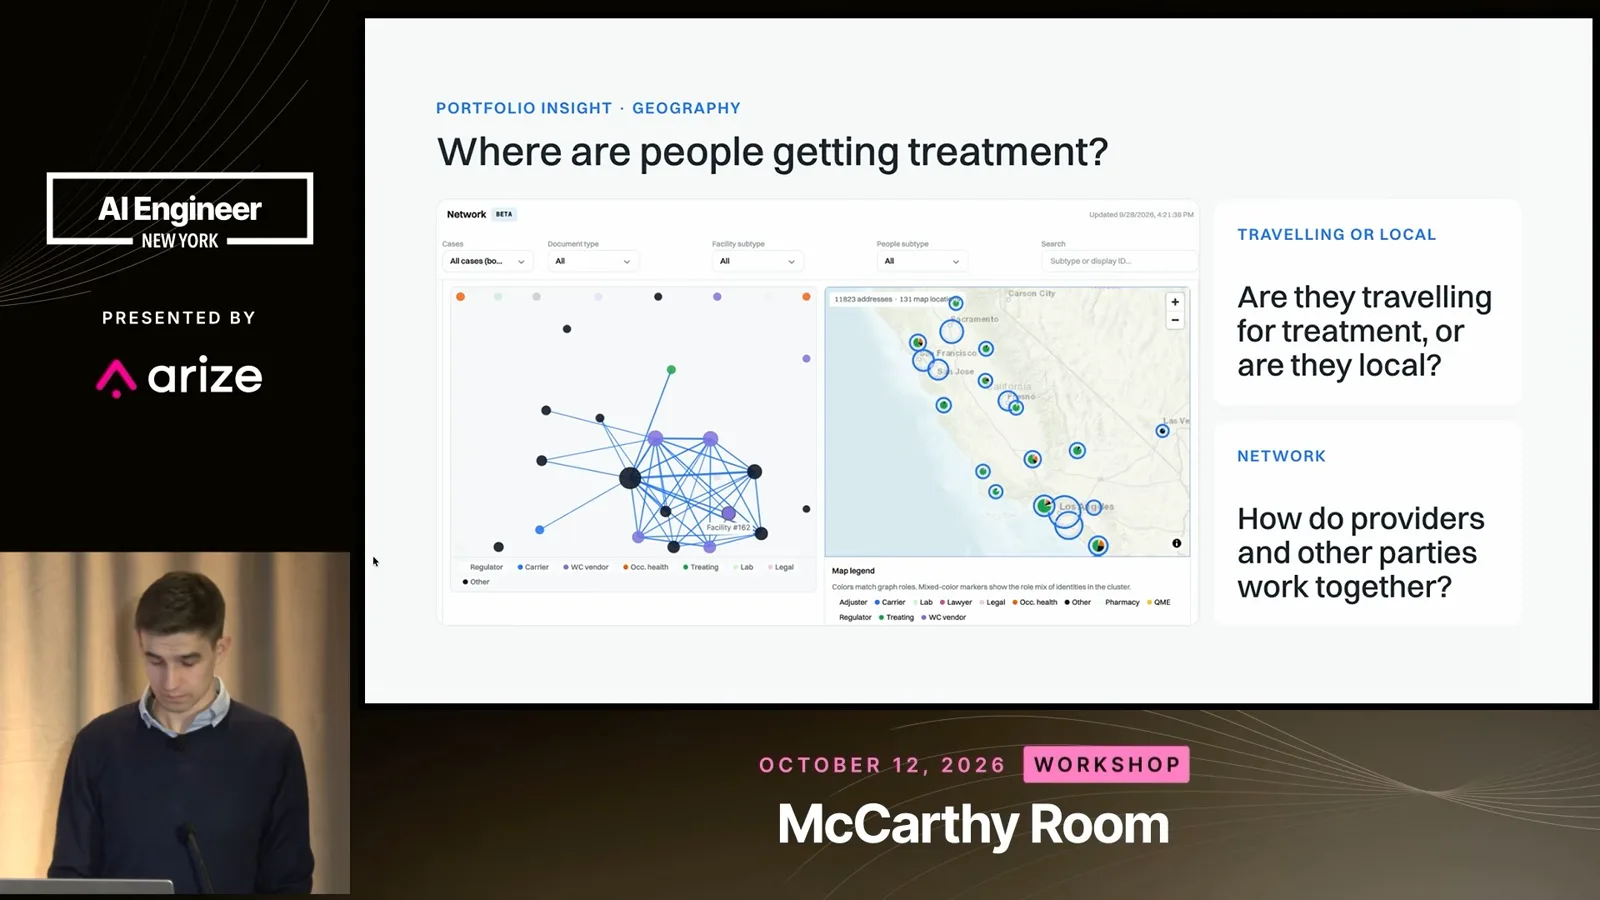
The example asks whether patients travel for treatment and how providers and other parties relate. A relationship or unusual pattern is a prompt for investigation, not a finding of wrongdoing.
Other analyses can look at diagnoses that co-occur and compare treatment charges over time. Differences may have clinical or contextual explanations, so cost should not be considered in isolation from outcomes.
A portfolio can test scenarios such as changes to networks and billing. These analyses can inform underwriting and resource allocation, but depend on representative data and sound assumptions.
The desired outcome is less delay and cost alongside better patient experience and care. Linkov says Wisedocs has seen savings in specific cases, while later noting that it cannot yet claim an industry-wide reduction in claim time.
Questions on implementation and oversight
He describes the processing pipeline, onboarding and human review.
In questions, I describe a layered pipeline: OCR and image processing, extraction and classification models, then summaries verified by people and further analysis. Real records require cleaning before a benchmark-like question can be answered.
Data sharing differs across business lines and organizations. Portfolio insights depend on the permissions, systems and goals of the particular customer.
For onboarding, we compare a small set of customer examples with what the system extracts. Even a date needs a precise definition: does the customer mean the injury date or the filing date?
If initial cases work, the next steps may include a broader pilot and integration with upstream systems. Capabilities and integration requirements vary, so a clear business objective is important.
Linkov says Wisedocs surfaces issues such as conflicting diagnoses for human decision-makers and aims to make its pipeline auditable. Human review helps, but alone does not establish regulatory compliance; applicable requirements still need assessment.
Customers have different priorities, including reducing backlogs and administrative or legal costs. Linkov says the team starts with a concrete operational problem and explores broader insights later.
Not every task requires a large language model. Classification and extraction models can be appropriate where accuracy, cost and hallucination risk matter; the team also trains some of its own models.
Linkov distinguishes individual customer case studies from population-wide evidence: the company cannot yet claim that it has reduced average claim duration for every patient.
A first notice of injury is only a starting point. A full review may require reconstructing records across years, name changes, locations and providers, with timelines varying by jurisdiction.
More from this channel
 21:32EN
 AI Engineer· Oct 29, 2026Shy Ruparel on AI agent reliability and recovery after failuresShy Ruparel · TemporalTemporal’s survey finds a gap between frequent agent use and dependable deployment. Ruparel demonstrates a synthetic payout workflow that resumes after workers stop.
 14:50ENAI Engineer· Oct 29, 2026Cole Gannaway on code review, cross-repository risk and AI software factoriesCole Gannaway · QodoA one-line rename can pass local checks while affecting distant clients. Qodo’s Cole Gannaway explains how review context, shared rules and independent agents can expose those risks.
 11:47ENAI Engineer· Oct 29, 2026Revolut’s David Abitbol on self-hosting AI coding models at scaleDavid Abitbol · RevolutAbitbol shares engineering delivery trends, GPU-serving costs and latency tuning, then describes controls for operating the tools in a regulated bank.
 21:47ENAI Engineer· Oct 28, 2026Patrick Smyth on Open-Source Supply Chain Security in the AI EraPatrick Smyth · ChainguardChainguard’s Patrick Smyth discusses faster exploitation, malware in dependencies, zero-days and the expanding attack surface around developer workflows.
 14:09ENAI Engineer· Oct 28, 2026Taylor Luttrell-Williams on Finding Logic Vulnerabilities with SonarQube Hunter AgentTaylor Luttrell-Williams · SonarSonar’s Taylor Luttrell-Williams explains how a security agent maps a codebase, investigates logic flaws and presents validated findings alongside conventional scans.
 16:29ENAI Engineer· Oct 28, 2026Chris Vela on Benchmarking vLLM Configurations with Runpod BenchPodChris Vela · RunpodRunpod’s Chris Vela demonstrates a dashboard for comparing LLM serving configurations and choosing performance settings with workload-specific data.